What’s New?

Midwifery Saves Lives: Why New Jersey Must Expand Access to Midwifery Care

Posted on July 3, 2025

winifred headshot
Winifred Smith-Jenkins
Director of Early Childhood Policy and Advocacy

Too many mothers and babies in New Jersey are dying, and it doesn’t have to be this way. Midwifery care is a proven, life-saving solution. But outdated laws, systemic barriers, and a lack of awareness are limiting access to this vital care.

A Forgotten Legacy of Care

For centuries, midwives were the primary providers of childbirth care in the United States. Before hospitals became common, childbirth happened at home with the help of skilled midwives. Many of these midwives were enslaved African women, Indigenous women, and immigrants who passed down knowledge through generations and provided trusted care in their communities.

Known as “granny midwives,” Black women in the South cared for mothers in rural and low-income communities well into the 1940s.These midwives provided prenatal education, labor support, delivery, and postpartum care at a time when hospitals were not accessible or welcoming to everyone. Their care kept communities alive and mothers safe.

2025 election badge2

Let's make children and their
families the center of the
2025 Election Campaign.

Starting in the early 1900s, hospitals and male doctors began to take over childbirth care. Public health campaigns and new licensing rules, often shaped by racism and bias, pushed midwives out by calling their work outdated or unsafe, without much proof. As a result, trusted community-led models of maternal care that worked for generations were lost.

Bringing midwives back into the center of maternity care isn’t just a return to tradition. It’s a matter of equity, cultural respect, and saving lives, especially for the families most at risk.
It's a Matter of Justice - Maternal death

What Exactly Is a Midwife?

A midwife is a highly trained clinical professional who specializes in healthy pregnancy, labor, birth, and postpartum care. They provide holistic, respectful, and culturally responsive care that centers around patient autonomy, trust, and informed decision-making.

Midwives are different from other birth workers: 

  • Midwives are not doulas – Doulas offer emotional and physical support, not clinical care.
  • Midwives are not OB-GYNs – OBs are trained as surgeons to manage high-risk pregnancies and complications.
  • Midwives are essential to a modern, integrated maternity care system that meets the needs of diverse families.

The Research is Clear: Midwives Save Lives

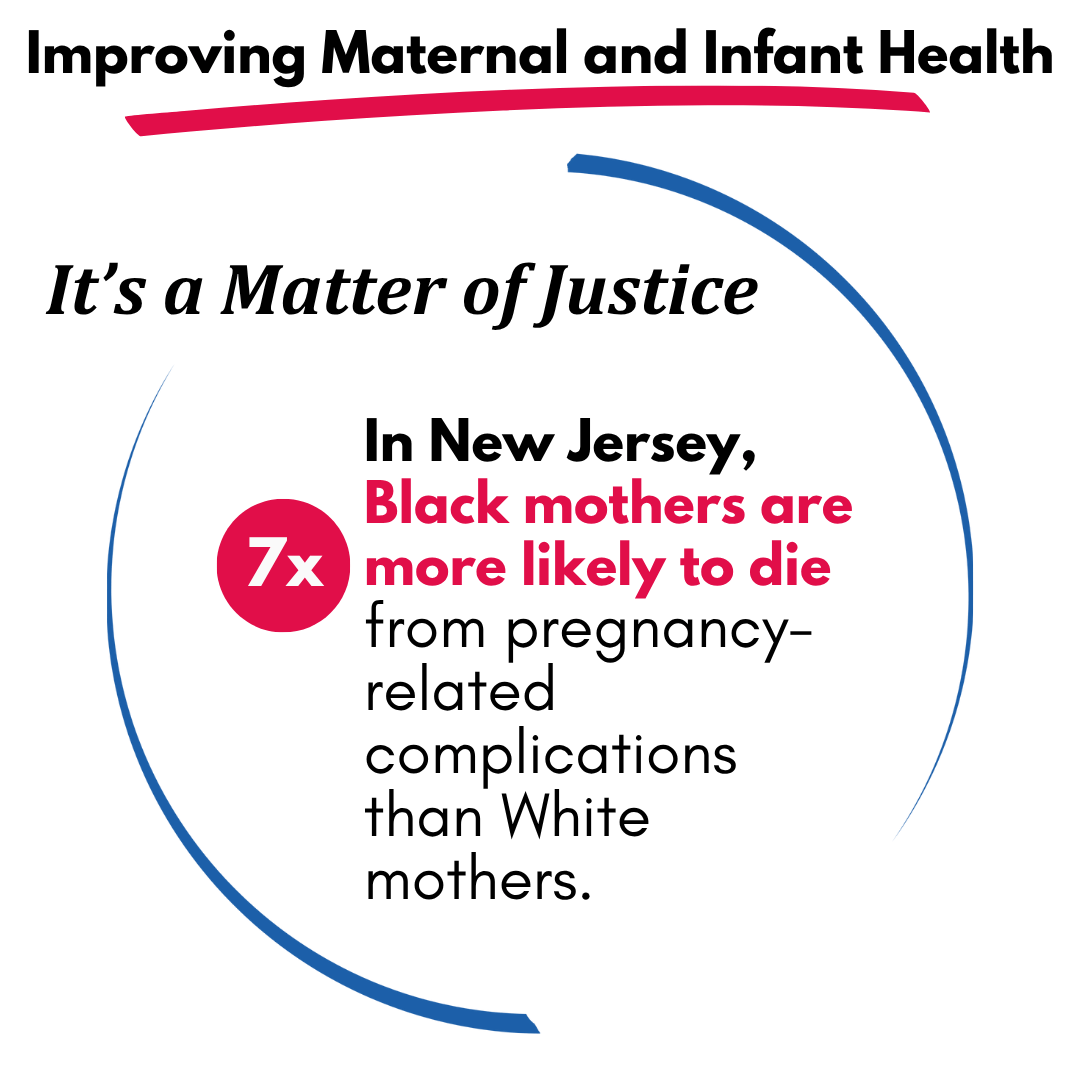
Research overwhelmingly shows that midwife-led care improves outcomes for mothers and babies; especially for Black families, who face the highest rates of maternal and infant mortality in New Jersey.

  • States with stronger midwifery integration have:
    • Lower rates of neonatal death, preterm birth, and low birthweight
    • Better outcomes for Black mothers and infants
  • Midwife-led continuity of care reduces fetal loss and neonatal death by up to 16%
  • Countries with strong midwifery systems (e.g., the UK, Norway) have significantly lower neonatal mortality than the U.S.
  • Midwifery practices—like delayed cord clamping, early breastfeeding, and reduced unnecessary interventions—support healthier newborn transitions

Barriers in New Jersey

Considering the benefits of midwives, New Jersey makes it hard for them to practice. The result? Families lose access to choices and the care they need.

Some of the biggest barriers: 

  • Restrictive laws prevent midwives from practicing independently
  • Midwives face burnout and a lack of supportive infrastructure
  • There is a shortage of racially and culturally diverse midwives
  • Aspiring midwives lack accessible training and mentorship pathways
  • Consumers, especially in underserved areas, lack access to midwifery care

New Jersey recognizes three midwifery credentials:

  • Certified Nurse Midwife (CNM) – Must be an RN and complete graduate midwifery training
  • Certified Midwife (CM) – Similar to CNM but with a non-nursing health science background
  • Certified Professional Midwife (CPM) – Trained through accredited programs or apprenticeship, often focused on home and birth center deliveries

Only CNMs and CMs can work in hospitals, but under the supervision of doctors. CPMs often cannot get paid or included in care networks, even though they are qualified. These limits make it harder for families to access the care they need.

Policy Solutions We Need Now

To improve maternal and infant health outcomes, New Jersey must:

  • Grant full practice authority to CNMs and CMs
  • Integrate and reimburse CPMs fairly
  • Establish an independent midwifery licensing board
  • Improve home-to-hospital transfer protocols
  • Expand pathways and scholarships for future midwives, especially midwives of color
  • Raise public awareness about the midwifery model of care

It’s a Matter of Justice

These outcomes are not inevitable. They are the result of systemic failures that we have the power to change. Expanding access to midwifery care is a critical, evidence-based solution.

What to Ask Candidates This Election Year

This election year, ask every candidate for governor:

  • What will you do to expand access to midwives?
  • How will you improve maternal and infant health for all families in New Jersey?

The future of maternal and infant health depends on bold, inclusive leadership, and midwifery must be part of the solution.

U.S. House of Representatives Moved the Federal Budget Process Forward

Posted on July 1, 2025

Last Thursday, the U.S. House of Representatives passed the “One Big Beautiful Bill Act” along party lines 215 (R)/214 (D).  The bill now moves to the U.S. Senate for their consideration. If H.R. 1 becomes law, several provisions of the bill will have a serious and devastating impact on NJ FamilyCare (which is funded by Medicaid) and the Supplemental Nutrition Assistance Program, or SNAP. Below are highlights. There are also provisions related to tax credits and student loans, which will impact children, youth, and families. We will update the ACNJ website as we learn more, so continue to check in.

Medicaid Related Sections

Almost 20% of New Jersey residents have health insurance coverage through NJ FamilyCare, which is funded by federal and state Medicaid dollars, as well as the federal Children’s Health Insurance Program (CHIP). This includes over 860,000 children. H.R. 1 will “save” nearly $700 billion in spending over the next 10 years by imposing additional eligibility requirements or restricting eligibility, thus reducing the number of people being covered by state public health insurance programs like NJ FamilyCare. H.R. 1 includes the following provisions:

  • Impose 80 hours of work or community engagement activities, such as education or volunteer service, for individuals ages 19 to 64 applying for coverage or enrolled through the Affordable Care Act expansion group, no later than December 31, 2026. This population is commonly referred to as the Medicaid expansion population. ACNJ was pleased to see an exemption in the bill for pregnant women, individuals under the age of 19 or over the age of 64, foster youth and former foster youth under the age of 26, members of tribes, and individuals who are considered “medically frail.” Individuals will have to verify that they are exempt.
  • Reduce retroactive coverage for Medicaid and Children’s Health Insurance Program (CHIP) to one month from three months as of December 31, 2026.
  • Require redetermination of eligibility every six months for the Medicaid expansion populations to begin on December 31, 2026.
  • Freeze current amount of provider taxes for states.
  • Require states to impose co-pays for Medicaid expansion adults with incomes over 100% of the federal poverty level (FPL). This cost-sharing may not exceed $35 per service. Exempted services include: primary care services, mental health care services, or substance use disorder services.
  • Impose new penalties for states that provide healthcare to undocumented immigrants. H.R. 1 would reduce the federal Medicaid expansion match rate from 90% to 80% for states like New Jersey that use state funds to provide health coverage for children, regardless of their immigration status, or pregnant adults covered under the Medicaid option for these groups.

Supplemental Nutrition Assistance Program (SNAP) Related Sections 

Close to 360,000 New Jersey children participate in SNAP currently. The House Resolution will reduce spending on SNAP by approximately $267 billion over the next ten years by restricting eligibility and shifting a greater percentage of the cost for both the benefit and administration of SNAP to the states.

Currently, the actual SNAP benefit is paid with federal dollars. H.R. 1 shifts 5% of the benefit and an additional 25% of the administrative costs to the states. According to the Center on Budget and Policy Priorities, if every state paid 5% of food benefit costs last year, states would have needed to collectively pay about $4.7 billion. The New Jersey Department of Human Services estimates that the additional 25% of administrative costs being shifted to the states will cost New Jersey counties an additional $78 million. Following are SNAP related provisions:

  • Limit the frequency of updates to the Thrifty Food Plan (TFP)—the basis for calculating SNAP benefits—to once every five years, requiring cost neutrality in updates.
  • Expand work required for able-bodied adults without dependents, raising the age from 54 to 64, and narrow the definition of a dependent child to those under the age of 7, limiting caregiving exemptions.
  • Restrict the automatic qualification for utility deductions in SNAP calculations to households with elderly or disabled members and limit income exclusions for state energy assistance.
  • Require states to contribute at least 5% toward SNAP benefit costs starting in FY 2028, with higher contributions (up to 25%) required for states with high SNAP error rates. Currently, the federal government pays 100% of the SNAP benefit.
  • Increase in the state’s share of administrative costs for implementing SNAP to 75%.

Ways and Means Bill Sections 

  • For the Child Tax Credit
    • Temporarily increase the Child Tax Credit to $2500 until 2028 and then return to $2000.
    • Set the refundable portion of the credit to $1400.
    • Require that individuals have earned income to be eligible for the credit.
    • Require a social security number for children, tax filers, and the tax filer’s spouse if married.
  • Temporarily boost the standard deduction — a $1,000 increase for individuals, bringing it to $16,000 for individual filers, and a $2,000 boost for joint filers, bringing it to $32,000. The deduction reduces the amount of income that is actually subject to income tax.
  • Increase the State and Local Tax (SALT) cap to $40,000 for incomes up to $500,000, with the cap phasing downward for those with higher incomes. Also, the cap and income threshold will increase 1% annually over 10 years.
  • Create a tax credit for school vouchers.
  • Parents or guardians who open new “Trump” accounts for their children will receive $1,000 from the federal government for babies born between Jan. 1, 2024 and Dec. 31, 2028. Families could add $5,000 a year, however, funds cannot be withdrawn before age 18, at which time they could access up to 50% of the money to pay for higher education, training, and first-time home purchases. At age 30, account holders have access to the full balance of the account for any purpose.

Pell Related Sections

  • Eliminate Pell Grant eligibility for less-than-half-time students.
  • Raise the definition of “full-time” to 15 credits per semester to get full Pell (from the current 12 credits).
  • Eliminate Stafford subsidized loans.
  • Eliminate graduate student PLUS loans and limit parent PLUS loans.
  • Eliminate existing income-contingent repayment plans and create a single income-based repayment plan, increasing the percentage of discretionary income and the number of payments needed before a loan can be forgiven.
  • Prevent the Department of Education from promulgating regulations that increase loan subsidy costs or are economically significant (no new debt relief regulations).
  • Clarify that payments made by new borrowers on or after July 1, 2025, who are serving in a medical or dental residency, do not count as a qualifying payment for purposes of the Public Service Loan Forgiveness Program.
  • Cap federal loans at the median cost of the student’s program of study.

What about the kids? 2025 Social Media Campaign

Posted on June 30, 2025

What about the kids logo outline

Your Voice Matters

Ask New Jersey candidates "What about the kids?" Help us get these issues on their campaign agendas. Share the posts below and make sure to tag candidates in your district.

Because better outcomes for children lead to thriving communities and a stronger economy when we invest in:

Facebook Feed Posts
Maternal & Infant Health
Child Care
Positive Youth Development
Instagram Feed Posts
Twitter Feed Posts
Maternal & Infant Health

Child Care

Positive Youth Development

Investing in Positive Youth Development to Address NJ’s Youth Mental Health Crisis

Posted on June 30, 2025

Will NJ's Future Governor Address Youth Mental Health?

Isaiah-Fudge-2024_5-cropped-web
Isaiah Fudge
Director of Positive Youth Development

For more information on this topic, contact Isaiah at ifudge@acnj.org.

Young people are struggling to cope with stress, anxiety and depression, and it’s persistently showing up in their daily lives, especially post-COVID. New Jersey is facing a mental health crisis. It's time the state prioritizes investment in positive youth development (PYD) to address and reduce mental health issues early, before they lead to more serious problems.

In June 2023, Rutgers’ New Jersey State Policy Lab found:

  • 42% of high school student respondents felt sad or hopeless, with the percentage among middle school respondents reaching 50%.
  • 37% of youth were seen as not “flourishing” (showing interest and curiosity; remaining poised when facing new challenges; and being able to complete tasks they start).
  • 23% of children were reported to have an emotional, mental, developmental, or behavioral issue.  

Beyond the most visible consequences—violence, self-harm, and youth detention—these issues can lead to declining academic performance, chronic absences, or disengagement from school altogether.

Nearly 24,000 or 5% of New Jersey youth are disconnected from school and 15% of students are chronically absent.

2025 election badge2

Let's make children and their
families the center of the
2025 Election Campaign.

Our Schools: Underequipped to Meet the Mental Health Needs of Youth

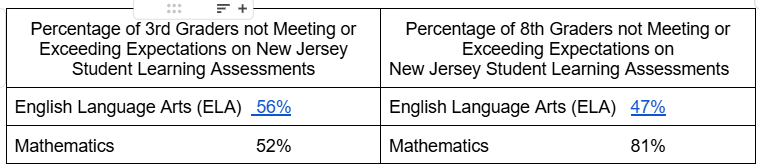
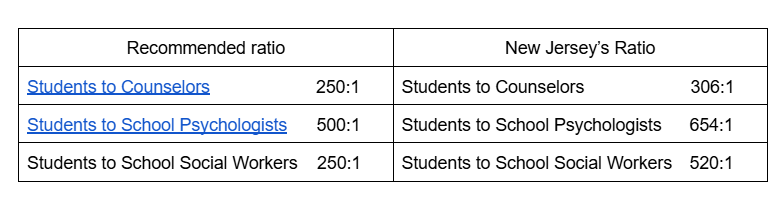
Not only are there gaps in resources, but access to those essential supports can also be difficult. Nowhere is this challenge stronger than in schools, where kids spend most of their time. While struggling with teacher shortages, the crisis is magnified by the lack of mental health professionals.

New Jersey’s school-based mental health professionals-to-student ratios are all beyond recommended ratios. These high ratios do not take into account that school psychologists and social workers are often overburdened with Child Study Team duties like assessment, evaluation, and IEP case work management, limiting their capacity to provide actual mental health supports to students.

Worse yet, despite recognizing the need for increased access to youth mental health supports, Governor Phil Murphy recently shared that the U.S. Department of Education has canceled nearly $1 billion in nationwide school-based mental health funding. This is likely to widen an already large gap in supports for New Jersey’s nearly 1.4 million students.       

Beyond the School Walls: Community Supports

Although there are some accessible resources to assist youth with their mental wellness, many of them are mostly available during emergency situations. But to curb the mental health crises, support services are needed to address issues before a problem becomes an emergency.

Throughout New Jersey, in 15 locations, there are regional hubs focused on supporting mental wellness for youth. New Jersey’s Statewide Student Support Services (NJ4S) is a preventive initiative with three tiers of services. Services in the first tier are available for all students in the state, their parents and school faculty. These include workshops on substance use, conflict resolution and lifestyle changes to improve mental health. The program also offers short-term, youth treatment through their tier 2 and 3 levels, available via referral from schools.

Although NJ4S can be a great resource, supports that emphasize positive youth development are needed to address, early on, the issues causing mental health issues and their effects.

Investing in the Whole Child: Fostering Learning and Mental Wellness

An enhanced whole-child approach in schools is all about tailoring support and interventions to meet the unique needs of every student, which ultimately cultivates learning. This approach is strongly complemented by positive youth development (PYD), an initiative that leverages the strengths of young people and their communities to support their holistic growth across areas like safety, health, and education.

Investing in PYD not only helps cultivate student learning but also plays a crucial role in promoting mental health wellness. Two of the most effective whole-child initiatives are social-emotional character development (SECD) programs and community-based violence intervention and prevention (CBVIP) strategies. These initiatives directly contribute to creating supportive environments where students can thrive both academically and emotionally.

Social-Emotional Character Development – This whole-child approach supports youth mental wellness through creating the conditions for youth to be their authentic selves. 

Community-Based Violence Intervention and Prevention – This whole-child initiative addresses the root causes of violence by providing wrap-around supports to at-risk students. Specifically, CBVIP, among other issues, addresses lack of housing, employment, and even access to food, effectively mitigating some of the factors that lead to poor mental health and ultimately catalyze violence. However, funding for this initiative has been cut by $811 million at the federal level leading to a $35 million shortfall here in NJ. With all the work resulting in consistent decreases in gun-violence in 2023 and 2024, its sustainability is now being threatened.  

What can you do?

Ask the gubernatorial candidates about their plans for ensuring our youth have mental wellness. Specifically:

  • What will you do to ensure NJ’s students have access to more mental health professionals while in school?
  • What is your plan to expand and sustain the best practices that promote healthy, holistic youth development in and around schools?

ACNJ Testimony to Senate Education Committee on Bill S4476

Posted on June 23, 2025

Winifred Head Shot2

Winifred Smith-Jenkins
Director of Early Learning Policy and Advocacy

Bill S4476 permits awarding of contracts for certain preschool education services by resolution of board of education; extends maximum length of preschool education services contracts to three years. Identical Bill Number: A5780

To: Senate Education Committee

From: Advocates for Children of New Jersey (ACNJ)

Date: May 12, 2025

RE: ACNJ’s Testimony on S4476

Dear Chairman Gopal and Members of the Senate Education Committee:

My name is Winifred Smith-Jenkins, and I serve as the Director of Early Childhood Policy and Advocacy at Advocates for Children of New Jersey. Thank you for the opportunity to testify in strong support of Senate Bill 4476.

This bill is a critical next step. It removes a significant bureaucratic barrier that hinders the expansion of high-quality preschool in New Jersey. ACNJ has long supported a mixed delivery system—one that includes community-based providers as essential partners in delivering early childhood education. S4476 helps advance that goal by simplifying the contracting process and extending contract terms to three years.

Importantly, multi-year contracts give providers something they’ve long needed—stability. When a provider has a contract that goes beyond a single year, it becomes a tool they can take to the bank to secure a loan, make much-needed infrastructure upgrades, purchase furnishings, and invest in high-quality classroom materials. It helps them manage the shortfalls that often come in June, when only a partial payment might arrive, but all their bills—staff salaries, rent, utilities—are still due.

This bill provides assurances that were once missing. It brings peace of mind, helping providers plan and grow confidently, knowing the partnership with their local school district isn’t just a one-year experiment, but a long-term commitment to our youngest learners.

We urge your support for S4476. Let’s give providers the foundation they need to deliver strong, stable preschool programs for New Jersey’s children.

Thank you.